


Getting out of bed in the middle of the night to use the bathroom is common, especially with age. But the condition, known as nocturia, can be more than a nuisance: repeated awakenings may be associated with a range of medical problems and with an increased risk of falls and possibly fractures.
Under the International Continence Society’s formal definition, waking from sleep once to urinate is enough to qualify as nocturia. In practice, however, doctors tend to pay more attention to two or more nighttime trips, particularly when the pattern is new or disrupts sleep.
Gallery

Nocturia is waking from sleep one or more times during the night to urinate
(Photo: shutterstock)
Dr. Leonid Boyarsky, a urologist with Meuhedet Health Services, says the need for evaluation depends not only on the number of awakenings but also on their impact on quality of life.
“If someone gets up once a night and it doesn’t bother them or affect them, it isn’t necessarily a problem,” he says. “But some people have difficulty falling back asleep even after waking once or twice. When the awakenings become a nuisance that damages sleep and next-day functioning, it is worth investigating.”
Waking every hour or two can interrupt both overall sleep continuity and deep sleep, he notes. Evaluation usually begins with questions about sleep hours, fluid intake during the day and evening and existing sleep disorders.
“One of the important questions is whether the person wakes up because they need to urinate, or urinates because they are already awake,” Boyarsky says. “It is not always possible to distinguish between the two immediately, but targeted questioning can help clarify what is happening. Sometimes the main problem is actually sleep quality, and that is what needs treatment.”
Nocturia becomes more common with age
The prevalence of nocturia rises with age. According to a clinical review in the U.S. National Library of Medicine database, about half of people aged 65 and older wake at least once a night to urinate, while around one-quarter wake twice or more.
 Dr. Leonid BoyarskyPhoto: Meuhedet spokesperson's office
A Japanese study published in 2013 in the Journal of Urology illustrates how common the condition is among older adults. It included 4,427 people aged 65 and older, with 3,685 completing questionnaires both at the start of the study and one year later.
The proportion reporting nocturia rose from 47% to 50.3% over that period.
During follow-up, 20% of participants who had not initially experienced nocturia developed it. Among those who already had nocturia, the condition resolved in 15.4%.
Men, people with a higher body mass index, those whose urinary symptoms worsened and those who developed overactive bladder were at higher risk of developing nocturia. The likelihood that it would resolve was lower among men, older participants, people with more severe urinary symptoms and those who developed overactive bladder.
Because the study was observational and relied on self-reported questionnaires, it can identify associations but cannot prove cause and effect.
One explanation for the increase in nocturia with age involves the body’s regulation of urine production. At night, the body normally releases more antidiuretic hormone, or ADH, which helps the kidneys concentrate urine and reduce its production.
As people age, that nighttime rise in ADH may weaken, allowing the kidneys to produce more urine during sleep. The condition is known as nocturnal polyuria. The amount and timing of fluid intake, along with caffeine, alcohol and certain medications, can also contribute.
Other possible factors include diabetes, overactive bladder, an enlarged prostate and fluid buildup in the legs. When a person lies down, that fluid can return to the bloodstream and lead the kidneys to produce more urine.
It is not always a bladder problem
Boyarsky says that in men around age 50 and older, one of the first possibilities doctors consider is an enlarged prostate, which can cause urinary symptoms including repeated nighttime trips to the bathroom.
In women, one possibility is overactive bladder, whose symptoms may be less disruptive during the day but become far more noticeable at night.
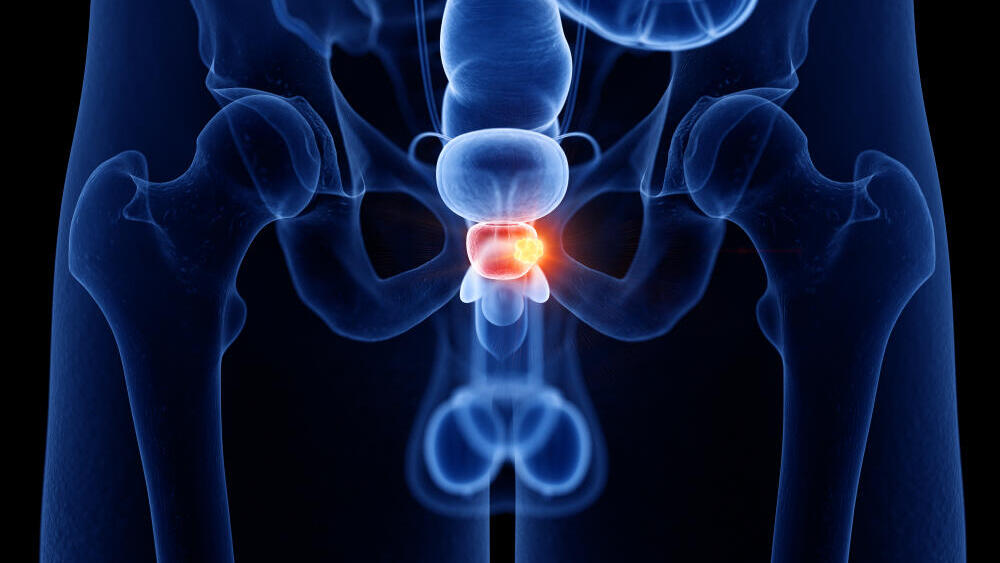
An enlarged prostate can cause urinary symptoms, including repeated nighttime trips to the bathroom
(Photo: Shutterstock)
Doctors also need to distinguish between frequent urination and the production of unusually large volumes of urine, and determine whether the problem occurs only at night or throughout the day.
Depending on the clinical picture, Boyarsky says other conditions may need to be considered, including heart failure and diabetes insipidus, a disorder of water balance caused either by insufficient ADH production or by the kidneys failing to respond properly to the hormone. It can result in the production of large amounts of dilute urine.
Nocturia can also be connected to sleep disorders.
Obstructive sleep apnea may affect hormonal mechanisms that regulate nighttime urine production. When doctors suspect it, Boyarsky recommends evaluation at a sleep clinic.
 Dr. Yariv StabholzPhoto: Sourasky Medical Center
Restless legs syndrome, which causes an urge to move the legs and unpleasant sensations that typically appear at rest and at night, may also contribute to awakenings followed by nighttime urination.
Dr. Yariv Stabholz, director of functional and reconstructive urology services at Tel Aviv Sourasky Medical Center, also known as Ichilov Hospital, says medications should be reviewed as part of the evaluation.
“Diuretics and certain medications used to treat diabetes can increase urine output and affect nighttime awakenings,” he says.
Identifying such factors can alter treatment recommendations, he adds, which is why doctors should review the patient’s medications before choosing therapy.
The link to falls and fractures
Among older adults who are already at risk of falling, particularly those with mobility limitations or cognitive decline, repeated nighttime trips to the bathroom deserve additional attention.
“Every trip to the bathroom at night, when a person is sleepier or more disoriented than during the day, can expose them to the risk of falling,” Boyarsky says.
Conditions such as osteoporosis should also be considered when assessing the potential consequences of a fall.
A systematic review and meta-analysis published in 2020 in the Journal of Urology examined the association between nocturia and falls and fractures. Of 5,230 potentially relevant publications, nine observational longitudinal studies were included in the analysis.

Repeated nighttime bathroom trips have been linked to an increased risk of falls, especially among older adults
(Photo: shutterstock)
Nocturia was associated with a 20% relative increase in the risk of falls, corresponding to an absolute annual risk difference of 7.5 percentage points among older adults.
Researchers also found a possible 32% relative increase in fracture risk, with an absolute annual risk difference of 1.2 percentage points. However, the association with fractures did not reach statistical significance.
The quality of evidence was rated moderate for nocturia as a predictor of falls and low for fractures. Evidence that nocturia itself directly causes falls or fractures was considered very low quality, meaning the findings do not prove a cause-and-effect relationship.
A cohort study published in 2010 in the International Journal of Clinical Practice followed 692 adults aged 65 and older who had not fallen in the year before the study. Their average age was 74.5, and 48% were women.
Nighttime urination frequency was recorded at the beginning of the study, while falls were assessed in telephone calls every six months for three years.
During follow-up, 214 participants, or 30.9%, reported at least one fall. Waking three or more times a night was associated with a 27% higher risk of falling in the initial analysis and a 28% higher risk after researchers adjusted for age, sex, race, duration of follow-up, diabetes and slow walking speed.
The study did not record what time the falls occurred or their circumstances, so researchers could not determine whether participants fell while walking to the bathroom.
They suggested that some falls could occur while people were walking drowsily in the dark, or during the day because of sleep deprivation, but those explanations were not directly tested. Nocturia frequency was also measured only once, and some falls may not have been reported.
First identify the cause, then choose treatment
“Nocturia is a symptom, not a disease,” Boyarsky emphasizes. “It can have urological and non-urological causes, and within each of those groups there are several possibilities. Before deciding on treatment, you need to understand what the problem is.”
One tool that can help is a fluid and urination diary. “The diary turns subjective complaints into data that can be measured and helps distinguish repeated awakenings from increased nighttime urine production,” Stabholz explains.
Patients are generally asked to record, for three to five full days, when they drink, what they drink and how much, along with the time and volume of each urination.
That record allows the doctor to examine drinking and urination patterns throughout the day and identify amounts or timing that may be contributing to nighttime awakenings.

Repeated nighttime urination can disrupt sleep and impair functioning the next day
(Photo: Shutterstock)
Evaluation also includes underlying medical conditions, medications, sleep disorders, neurological conditions, how long the problem has been present and whether it is constant or intermittent.
Shift work can also affect both sleep and urination patterns, Boyarsky says.
Stabholz adds that if changes to drinking habits or adjustments to medications do not help, further testing may be considered depending on the findings, including urinary tract ultrasound or urodynamic testing.
Such tests can help assess the structure and function of the urinary system and identify issues such as overactive bladder contractions, elevated pressures or urinary obstruction.
When testing indicates excessive nighttime urine production, treatment can be tailored accordingly.
Along with changes in fluid intake, Stabholz says that in appropriate cases doctors may consider medication that mimics the action of antidiuretic hormone. The treatment helps the kidneys reabsorb water and concentrate urine, reducing the amount produced at night.
Before turning to medication, experts recommend examining drinking habits. Reducing caffeine and alcohol in the evening and limiting fluids close to bedtime may help. Avoiding drinks for about two hours before bed and alcohol for roughly three hours beforehand may benefit some people.
For those with fluid accumulation in the legs, elevating the legs before bed and using compression stockings during the day may also help.
Patients should also ask a doctor or pharmacist whether any medications may be contributing, but should not change medication or its timing without medical advice.
Even food eaten in the evening can matter. “Some people eat soup or fruit in the evening and then wonder why they wake up at night,” Stabholz says.
Alongside coffee and alcohol, he says, people should also consider fluids contained in food and discuss the amount and timing of consumption with their doctor.
To reduce fall risk, experts recommend clearing objects and loose rugs from the path to the bathroom, using soft lighting, sitting on the edge of the bed before standing and installing grab bars when needed.
If nighttime urination begins suddenly, becomes more frequent or starts interfering with sleep and daytime functioning, medical evaluation is recommended.